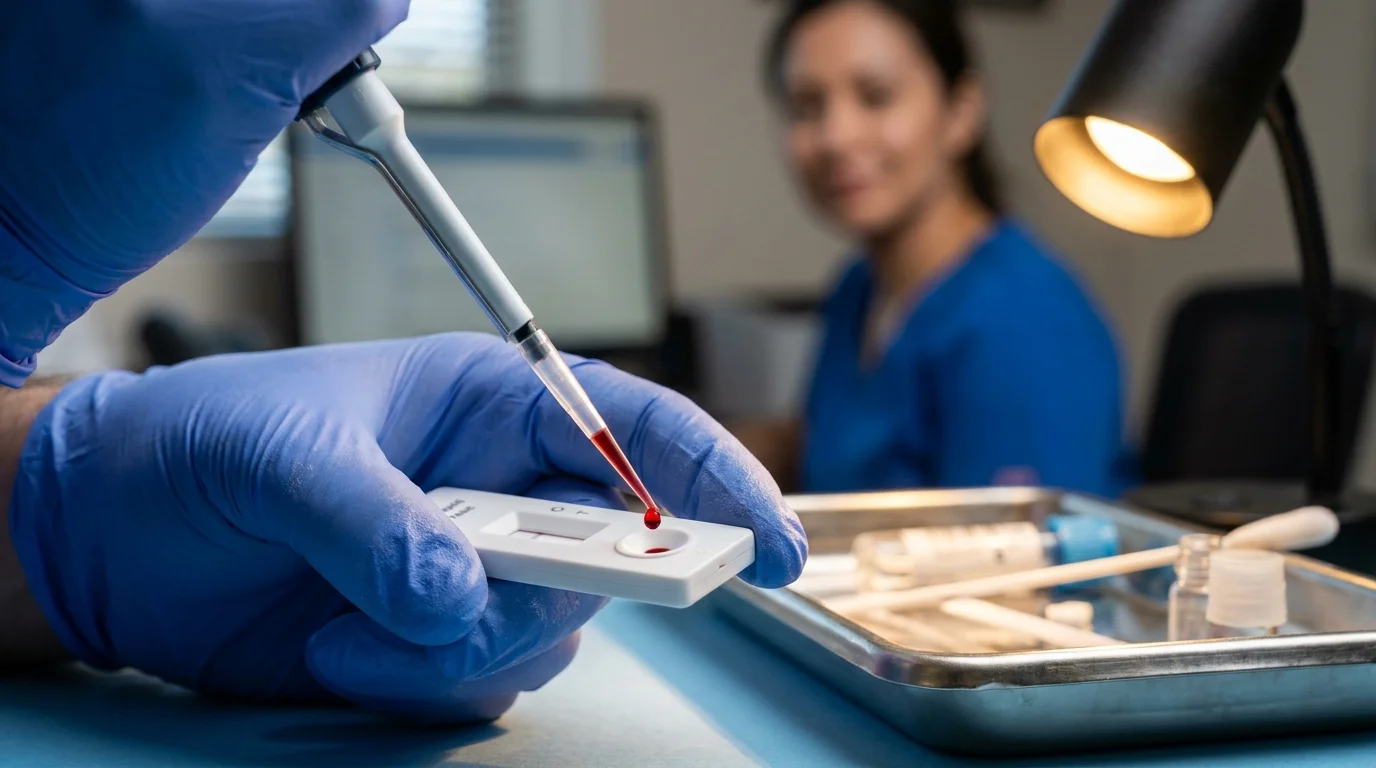
The persistent hum of overhead fluorescent lights, the faint smell of industrial citrus cleaner, and the low rustle of paper triage sheets make every urgent care waiting room feel identical. You sit with your knees drawn tight, nursing an ache behind your eyes that feels less like a common summer cold and more like a heavy iron weight pressing against your temples. When your turn arrives, you expect the standard tongue depressor, the routine flu swab, and a brief nod toward the exit.
Instead, the intake nurse pauses over her clipboard, looking past your forehead thermometer reading to ask a question that feels strangely out of place: where did your feet touch grass over the past two weeks? The intake monitors no longer just flag winter respiratory bugs; they now flash yellow alerts for mosquito-borne travel histories before you even step into an exam room.
Across the country, federal health directives have quietly pushed emergency rooms and neighborhood walk-in clinics to overhaul how they process unexplained fevers. What used to be dismissed as a rough bout of dehydration or an unseasonal summer virus is now triggering a rapid assessment protocol designed to catch viral transmissions days before standard lab cultures return.
You are witnessing a fundamental shift in front-line medicine, where the boundary between a routine domestic fever and a tropical viral infection has dissolved into the daily intake line.
The Shifting Geography of Viral Watchlists
For decades, American medicine treated mosquito-borne fevers as an imported anomaly—a souvenir brought home by international backpackers or relief workers returning from distant equatorial zones. That mental model worked when travel patterns were predictable and localized micro-climates remained stable throughout the long summer months.
Think of your immune system like a home plumbing system: when a pipe begins vibrating, you don’t assume the problem originated across the globe if the water pressure in your own neighborhood just spiked. The federal advisory pivot acknowledges that ambient transmission lines are moving, turning regional state borders and coastal weekend getaways into active monitoring corridors.
Clinics are no longer waiting for the traditional late-August seasonal peak to begin running screening panels. By restructuring triage questions to catch early platelet dips and distinctive joint tenderness right at reception, clinicians prevent the catastrophic misdiagnosis of treating a vascular viral infection with routine anti-inflammatories.
- Couch armrest leaning tilts the lower pelvis sparking grinding daily back aches
- Floor water bowls beside bedroom radiators restore smooth breathing and throat comfort
- Seated shoe lacing strips daily single-leg balance and silently weakens stabilizing ankle muscles
- Sternum knuckle taps halt racing heartbeats during sudden solitary panic surges
- Drinking pickle juice halts sudden midnight calf cramps across sixty fast seconds
When triage desks treat geographic exposure as a fluid map rather than a rigid passport requirement, your mild symptoms receive an accurate diagnostic pathway hours faster than standard intake would allow.
Dr. Marcus Reyes, a 46-year-old emergency department director in central Florida, saw the necessity of this shift firsthand when routine admissions began presenting with atypical joint pain and borderline-low platelet counts in late spring. “We were watching patients sit in observation for twelve hours under standard viral exhaustion protocols,” Reyes explains, reviewing his unit’s revised intake algorithm. “Once the federal advisories mandated asking about domestic Gulf travel and weekend outdoor exposure on the very first intake screen, our time-to-diagnosis plummeted from nearly two days down to twenty minutes.”
Three Profiles Reshaping Urgent Care Waiting Rooms
Emergency departments and urgent care centers do not treat every fever with the same broad brush. The overhauled screening protocol categorizes patients into distinct risk profiles to ensure rapid blood testing happens where it matters most.
The Regional Commuter
If you split time between southern metro hubs or spend weekends camping along coastal lowlands, your risk baseline is no longer considered zero. Triage nurses are trained to look past the absence of international travel stamps and focus on localized exposure windows. Catching early retro-orbital pain—that deep, dull ache seated squarely behind your eyes—prompts an immediate point-of-care platelet evaluation before you are sent home with generic advice.
The Island and Cruise Hopper
Short-haul vacations to the Caribbean or quick layovers in Puerto Rico often blur together once you return to your desk on Monday morning. Because symptom onset can lag by up to two weeks, intake staff now cross-reference common port-of-call schedules against your first day of fatigue. Identifying this window prevents clinics from confusing mosquito-borne transmission with simple travel exhaustion or cruise-ship stomach bugs.
The At-Risk Household Member
For older adults or individuals managing underlying vascular conditions, an unexpected viral spike demands immediate vigilance. In these cases, screening updates require care teams to bypass watchful waiting. Monitoring baseline fluid balance becomes the primary directive, ensuring that subtle capillary leaks or blood pressure fluctuations are caught before emergency stabilization is required.
Mindful Steps for Navigating the New Intake Line
Walking into an urgent care while feeling miserable can make clear communication difficult. Knowing what the new screening standards look for allows you to advocate for yourself without feeling overwhelmed.
Be ready to share your exact timeline rather than a vague estimate of when you started feeling worn down. Emergency medicine relies on precise intervals between environmental exposure and the first physical signs.
- Log your outdoor footprint: Note any state parks, coastal areas, or humid urban zones you visited within the last fourteen days.
- Track the fever curve: Record morning and evening temperatures on your phone rather than relying on memory.
- Describe pain locations precisely: Highlight aches behind the eyeballs, lower back stiffness, or sudden skin sensitivity.
- Hold off on NSAIDs: Avoid taking aspirin or ibuprofen until a physician confirms your platelet count, relying on simple cool compresses and clinician-approved alternatives instead.
The Clinical Intake Toolkit
Before heading to the clinic, prepare these specific data points for the triage nurse: your peak temperature reading in degrees Fahrenheit, the exact calendar day of your last outdoor exposure, an honest count of your daily fluid intake in ounces, and a clear list of any unexplained skin flushing across your chest or arms.
A Grounded Sense of Security in Everyday Care
Medical protocol updates often sound intimidating when distilled into institutional headlines, but their real-world impact is quiet and protective. They exist to strip away guesswork in the moments when you feel most vulnerable and drained.
Understanding that an intake nurse’s travel questions are a deliberate safety net—not an invasive interrogation—shifts your perspective from frustration to relief. You are not facing an unseen medical mystery; you are benefiting from a refined diagnostic net that catches subtle signs long before they spiral into critical emergencies.
“Modern triage works best when we stop waiting for severe complications to declare what a virus is, and start listening to the geography of the patient’s past ten days.”
| Key Point | Detail | Added Value for the Reader |
|---|---|---|
| Early Geographic Screening | Intake checklists now include domestic travel and coastal outdoor activity within 14 days. | Prevents premature discharge without proper viral blood work. |
| Platelet Monitoring Priority | Immediate complete blood counts (CBC) ordered for unexplained fevers with joint stiffness. | Rules out rapid micro-vascular complications early. |
| Medication Guardrails | Strict avoidance of ibuprofen and aspirin prior to definitive viral screening. | Eliminates accidental bleeding risks caused by platelet disruption. |
Frequently Asked Questions
Why are emergency rooms asking about travel if I haven’t left the country?
Federal health agencies updated protocols because transmission ranges for mosquito-borne illnesses have expanded into domestic southern and coastal corridors, making recent regional travel clinically significant.What is the signature symptom that sets this apart from a standard summer cold?
While both cause body aches and fever, mosquito-borne viral signs often feature a distinct, heavy ache directly behind the eyes and severe lower-back joint tenderness without typical nasal congestion.Why should I avoid ibuprofen before getting screened for an unexplained fever?
Certain mosquito-borne viruses temporarily lower your blood platelet count; taking non-steroidal anti-inflammatory drugs like ibuprofen can thin your blood further and increase internal bleeding risks.How quickly do symptoms appear after being exposed outdoors?
Signs typically emerge between four and ten days following an insect bite, which is why intake staff focus on your physical locations over the preceding two weeks.Can urgent care clinics run these screening tests on site?
Most modern walk-in clinics can perform immediate complete blood count (CBC) panels to check platelet levels within thirty minutes, referring more complex antibody tests to regional labs while keeping you safely monitored.



