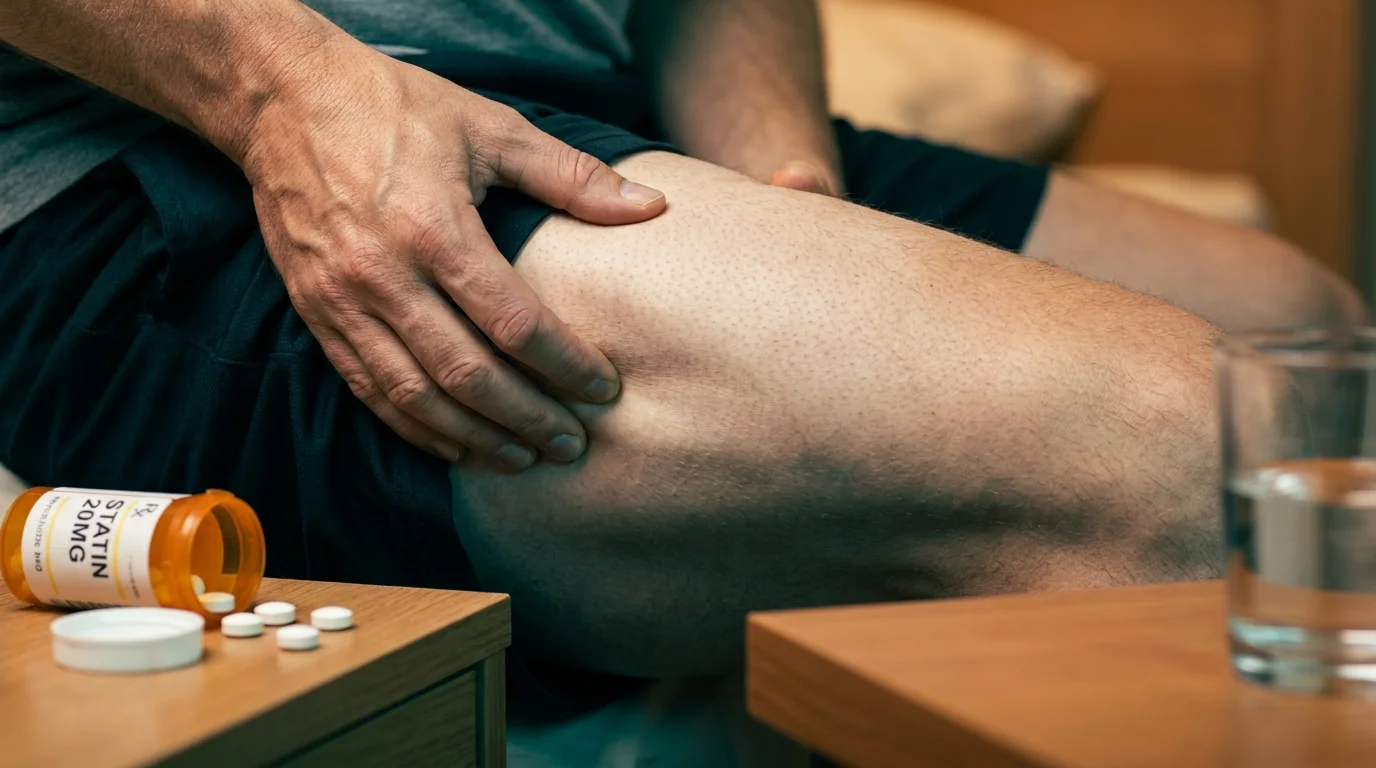
The amber bottle sits on the nightstand beside a sweating glass of water. At 10:45 PM, the bedroom is quiet, the furnace hums beneath the floorboards, and you twist open the childproof cap out of muscle memory. A single chalky tablet slides down your throat, just as the label instructs: take once daily at bedtime.
Seven hours later, the alarm cuts through the gray dawn, but your body refuses to match the room’s momentum. Swinging your feet over the edge of the mattress feels like dragging dry anchors through mud, your quadriceps and calves filled with damp river sand before your heels even meet the cold hardwood.
You shake it off as poor sleep, dry air, or the quiet wear-and-tear of another calendar year. Yet as the morning unfolds, a subtle metabolic drag trails behind you—stairs feel steeper, your coffee barely scratches the surface of your mental fog, and your legs remain leaden until noon. This is not ordinary fatigue; it is a pharmacokinetic bottleneck playing out across your muscle beds.
The Clearance Clock and the Night-Shift Liver
The golden rule of evening statin therapy was born in the era of short-acting compounds. Decades ago, first-generation agents targeted 3-hydroxy-3-methylglutaryl-coenzyme A (HMG-CoA) reductase—the liver enzyme responsible for churning out cholesterol—which ramps up its production during the midnight fasting hours. Taking your pill right before your head hit the pillow ensured peak drug concentration perfectly matched peak enzyme synthesis.
Today’s modern regimens rely on long-acting, lipophilic and hydrophilic molecules designed to persist in human tissue far longer than eight hours. When your liver is asked to filter, conjugate, and clear a potent dose while your peripheral circulation slows to resting nocturnal speeds, the system backs up like an overloaded drain. Instead of a swift, targeted hepatic uptake, circulating metabolites spill outward, lingering in peripheral skeletal muscle fibers right as you attempt to stand upright for the day.
When your hepatic clearance stalls during sleep, drug molecules cross the sarcolemma membrane of skeletal muscle cells, interfering with the electron transport chain inside your mitochondria. The result is a sharp drop in cellular adenosine triphosphate (ATP) renewal, leaving muscle tissue starved of immediate morning fuel.
- Avocado cooking oil pan searing triggers stinging sinus pressure and sudden afternoon brain fog
- Pushing off armrests accelerates leg muscle loss and triggers wobbly standing balance
- Bottled green juices spark shaky afternoon energy crashes and trigger ravenous snack cravings
- Outer palm pressing releases rigid neck stiffness and soothes burning shoulder knots
- Glossy tablet screens trigger sharp afternoon eyelid twitches by exhausting focal depth
The Clinical Shift: Dr. Marcus Vance’s Morning Discovery
Dr. Marcus Vance, a 56-year-old clinical pharmacologist based in Richmond, Virginia, began observing this persistent drag not in sedentary patients, but among the dedicated morning runners in his preventive cardiology cohort. Patient after patient reported that their 6:00 AM jogs had devolved into painful shuffles, marked by lingering calf cramps and an inability to warm up their bodies before work. When Vance analyzed their plasma profiles, he discovered that patients taking long-acting statins at 11:00 PM still showed near-peak systemic concentrations at 8:00 AM, paralyzing the natural morning cortisol surge that primes skeletal muscle for exertion.
Decoding Your Clearance Window: Three Metabolic Profiles
Your body does not metabolize bedtime pharmaceuticals on an arbitrary schedule set by a bottle label. How you handle your dose depends on your liver’s cytochrome P450 enzyme efficiency and your daily routine.
The Early-Morning Mover
If your feet hit the floor at 5:30 AM for a walk, a gym session, or a brisk commute, a late-night statin dose hits your bloodstream at the worst possible time. Your leg muscles demand explosive mitochondrial energy right when local drug concentrations are at their absolute apex. For this group, shifting the administration window under physician guidance often eliminates that distinctive lead-legged sensation within forty-eight hours.
The Slow-Clearance Phenotype
Individuals taking lipophilic formulations—which dissolve into adipose and muscle tissue rather than water—naturally retain active metabolites longer. Paired with common CYP3A4 inhibitors like morning citrus or blood pressure medications, late-night dosing creates a compounding spillover effect that suppresses daytime metabolic rate and leaves skeletal tissue persistently stiff.
The Shift-Worker and Delayed Sleeper
Taking a statin at midnight when your sleep schedule fluctuates throws off your liver’s circadian metabolic cycle. Bile production, blood flow, and glucuronidation slow dramatically outside standard daylight windows, causing the pill to sit in sluggish digestive pathways, prolonging absorption and extending morning lethargy well past midday.
Recalibrating the Dose Window
Addressing medication-induced heaviness does not mean abandoning cardiovascular protection. It requires aligning the medication’s peak concentration with your body’s periods of rest rather than your hours of movement.
Simple scheduling adjustments often restore natural morning vigor without compromising lipid management:
- Audit the Molecule: Check whether your prescription is a short-acting compound (which requires evening dosing) or a long half-life agent that maintains twenty-four-hour efficacy regardless of clock time.
- The Midday Shift: Under clinical supervision, slowly migrate long-acting doses toward late morning or early afternoon, ensuring peak systemic concentrations land during deep evening sleep rather than early dawn.
- Support Cellular Energy: Introduce mitochondrial cofactors like ubiquinol alongside daytime meals containing healthy dietary fats to preserve peripheral muscle ATP synthesis.
- Hydration Buffering: Drink sixteen ounces of mineralized room-temperature water before bed to support renal clearance pathways throughout the night.
By shifting your administration time by just four to six hours, you allow your skeletal muscles to wake up free from peak metabolic drag. Your legs feel lighter, your morning gait normalizes, and your natural daytime energy returns smoothly without unnecessary pharmaceutical friction.
Reclaiming Morning Rhythm
True cardiovascular wellness should not demand that you feel like a stranger in your own muscles each morning. Health is measured not solely by numbers on a lipid panel, but by your ability to step out of bed, move freely, and meet the day without feeling weighted down by your own remedies.
When you learn to view dosing schedules through the lens of human physiology rather than habit, clarity replaces frustration. A pill should work quietly in the background of your biology, protecting your future without draining the vitality of your present morning.
“Cardiovascular longevity means little if the treatment quietly strips away your physical desire to move your body every morning.” — Dr. Marcus Vance
| Key Point | Detail | Added Value for the Reader |
|---|---|---|
| Pharmacokinetic Mismatch | Bedtime doses peak during morning movement cycles rather than overnight rest. | Explains why leg heaviness strikes immediately upon waking rather than during sleep. |
| Half-Life Differences | Modern statins stay active for 14 to 30 hours, making strict bedtime timing obsolete. | Empowers you to discuss morning or midday dosing options with your physician. |
| Mitochondrial ATP Stall | High local tissue concentration temporarily slows cellular energy renewal in skeletal muscle. | Confirms that your morning fatigue is biological, not a personal lack of willpower. |
Frequently Asked Questions
Why do pharmacy labels universally recommend taking statins at bedtime?
The practice began with older medications like lovastatin and simvastatin, which have short half-lives of under three hours and work best when taken right before peak overnight cholesterol synthesis. Modern statins like atorvastatin and rosuvastatin have much longer half-lives and can be taken at any consistent time of day.Can changing my statin dose time cause cholesterol levels to rise?
Not if you are taking a long-acting compound with a half-life exceeding fourteen hours. These medications provide steady enzyme suppression over a complete twenty-four-hour cycle, meaning therapeutic protection remains stable regardless of whether you swallow the pill at 9:00 AM or 10:00 PM.How can I tell if my leg heaviness is statin-related or normal fatigue?
Statin-induced muscle drag typically presents bilaterally across large muscle groups like the quadriceps, calves, and glutes, feeling like deep physical weight rather than joint pain. It is often most pronounced during the first two hours after waking.Should I stop taking my statin immediately if I wake up feeling sluggish?
No, you should never discontinue a prescribed cardiovascular medication cold turkey. Instead, bring your morning symptom log to your prescribing doctor and request a conversation about dose timing, molecule substitution, or testing your liver clearance rates.Does coenzyme Q10 help with morning muscle heaviness?
Statins naturally deplete endogenous CoQ10 by inhibiting the same mevalonate pathway used to produce it. Supplementing with ubiquinol can often support muscle mitochondrial energy, though optimizing your dosing window remains the most direct fix.



